Respiratory infections are one of the commonest causes of death in patients with chronic lymphocytic leukemia (CLL). Immunodeficiency is one of the most important features of the disease. Severe hypogammaglobulinemia is a common complication, and even patients with early disease have an impaired ability to produce an antibody response to a novel antigen [1]. Even with a recall antigen like tetanus toxoid antibody responses were only seen in stage A patients in 4/14 patients and not at all in more advanced stage patients [2].
Although patients with CLL are advised to receive annual vaccination against influenza [3], the production of a protective antibody response is extremely uncertain. There have been three recent studies of attempts to increase responses by giving a second booster vaccination shortly after the initial dose. In the first [4] the response rate went from 14% to 35%; in the second [5] from 0% to 5%; and in the third [6] which included patients with other haematological malignancies, the response rose from 18% to 22%. In real life it is likely that the most beneficial effect of influenza vaccination for CLL patients is herd immunity, with spouses, relatives and friends being vaccinated
The cause of the immunodeficiency in CLL is not known. Although it is worse in more advanced patients, it precedes treatment and it precedes the development of hypogammaglobulinemia. It occurs very early in the disease, long before the lymphoid system is overwhelmed by infiltration with CLL cells.
One possibility is a defect in antigen presentation. The most important antigen presenting cells are dendritic cells. In CLL the circulating dendritic cell is severely defective and unable to stimulate an effective T cell response [7]. This defect seems to be due to the presence of the CLL cells, possible operating via one of the many cytokines (including IL-6, IL-10, VEGF and M-CSF) that CLL cells produce [8]. Nevertheless, when stimulated by an appropriate cytokine milieu it is possible stimulate and activate dendritic cells derived from the peripheral blood of CLL patients [9].
A new group of immune stimulants, the imidazoquinolones [10], act by binding to Toll receptor 7 on the surface of macrophages, inducing the secretion of the pro-inflammatory cytokines IFN-gamma, TNF-alpha, and IL-12. This local cytokine milieu favours the development of activated dendritic cells. One of the imidazoquinolones, Imiquimod, is licensed for the treatment of genital and perianal warts and for basal cell carcinoma, and is available as a cream to apply to the skin. The drug has also being investigated as an adjuvant in cancer vaccine studies where preliminary experiments demonstrate its capacity for activating dendritic cells and markedly enhancing the production of cytotoxic T lymphocytes [11, 12].
We propose to investigate the possibility that the application of Imiquimod to the site of a subcutaneous vaccination might enhance the immune response to influenza vaccine in patients with chronic lymphocytic leukaemia. In order, to see an effect of Imiquimod it will be necessary to give the vaccine subcutaneously rather than intramuscularly. Influenza vaccines are licensed for this mode of administration and although it is normally reserved for patients with bleeding disorders, it is equally efficacious. However, to control for the different route of administration and for the fact that CLL patients mostly belong to an older generation and might give a poorer response to vaccination because of this, we propose to offer subcutaneous influenza vaccination to patients’ spouses, measuring responses in a similar way. This would, in any case, be part of routine management to take advantage of herd immunity.
References
1. Hamblin TJ, Verrier Jones J, Peacock DB. The immune response to x 174 in man: iv primary and secondary antibody production in patients with chronic lymphatic leukaemia. Clinical and Experimental Immunology 1975; 21:101 108.
2. Sinisalo M, Aittoniemi J, Oivanen P, Olander R-M, Vilpo J. Response to vaccination against different types of antigens in patients with chronic lymphocytic leukaemia. Brit J Haematol 2001; 114:107-110.
3. Oscier D, Fegan C, Hillmen P et al. Guidelines on the management of chronic lymphocytic leukaemia. Brit J Haematol 2004; 125:294-317.
4. Jurlander J, de Nully Brown P, Skov PS et al. Improved vaccination response during ranitidine treatment, and increased plasma histamine concentrations, in patients with B cell chronic lymphocytic leukemia. Leukemia 1995; 9:1902-1909.
5. van der Velden AMT, Mulder AHL, Hartkamp A, Diepersloot RJA, van Velzen-Blad H, Biesma DH. Influenza virus vaccination and booster in B cell chronic lymphocytic leukaemia patients. Eur J Int Med 2001; 12:420-424.
6. Ljungman P, Nahi H, Linde A. Vaccination of patients with haematological malignancies with one or two doses of influenza vaccine: a randomized study. Brit J Haematol 2005; 130:96-98.
7. Orsini E, Guarina A, Chiaretti S, Mauro FR, Foa R. The circulating dendritic cell compartment in patients with chronic lymphocytic leukemia is severely defective and unable to stimulate an effective T-cell response. Cancer Res 2003; 63:4497-4506.
8. Orsini E, Pasquale A, Maggio R et al. Phenotypic and functional chatacterization of monocyte-derived dendritic cells in chronic lymphocytic leukaemia patients: influence of neoplastic CD19 cells in vivo and in vitro. Brit J Haematol 2004; 125:720-728.
9. Messmer D, Telusma G, Wasil T et al. Dendritic cells from chronic lymphocytic leukemia patients are normal regardless of Ig V gene mutation status. J Mol Med 2004; 10:7-12.
10. Stanley MA. Imiquimod and the imidazoquiniolones: mechanism of action and therapeutic potential. Clin Exp Dermatol 2002; 27:571-577.
11. Rechsteiner G, Warger T, Osterloh P, Schild H, Radsak MP. Cutting edge: priming of CTL by transcutaneous peptide immunization with Imiquamod. J Immunol 2005; 174:2476-2480.
12. Warger T, Osterloh P, Rechsteiner G et al. Synergistic activation of dendritic cells by combined Toll-like receptor ligation induces superior CTL responses in vivo. Blood. 2006; 108:544-550.
Wednesday, October 04, 2006


Sunday, October 01, 2006
Spending on health
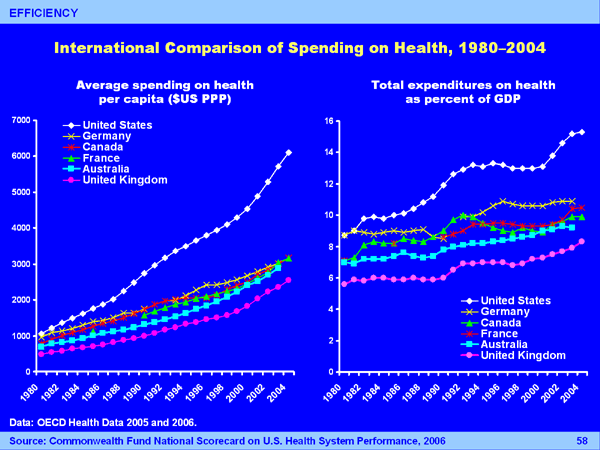
This graph is referred to by my son's new 'work' blog. I find the figures quite surprising. In the UK in 1997 Tony Blair's warning was 90 days to save the NHS. It is certainly true that there has been a marked increase in spending on health, but after nearly 10 years the UK is still bottom of the heap as far as health spending is concerned.
Everybody has had to increase spending to keep up with what can be done.
A recent feature on BBC TV looked at the best public services in the world. For public transport they chose Portland, Oregon, but for health they chose Cuba. Astonishing! Cuba has no access to modern drugs and its health workers are paid a pittance. Nevertheless, life expectancy in Cuba is higher than in the US. Life expectancy in the US is an anomaly, probably the result of inadequate public health services for the poor. A high infant mortality impacts more significantly on life expectancy than excellent care for the elderly; an individual loses 70+ years rather than 3-4 years. So when the indigenous poor have next to no ante-natal care and when there are areas where the commonest cause of maternal death is gunshot wound, these impact far more heavily on the statistics than all the rituximab in the world.
All health care systems want to get the best value for money, but how you collect the statistics affects the result. Suppose the figures were collected not from cradle to grave but from conception to grave. What price Roe v Wade then?
Public health measures give you more bangs per buck than any other health intervention. Edward Jenner and John Snow had more impact than Harvey Cushing and William Osler. Of course, America has clean water and smallpox has been eliminated, but without full vaccination for children and good housing and nutrition for the poor, the acute health care system gets overrun by preventable disease.
I believe I saw somewhere that America spends more on Medicare and Medicaid and front-line free-care in the ERs of County Hospitals per head of population, than the UK spends on the whole NHS. What I am getting around to saying is that despite spending a far smaller proportion of the GDP on health, Britain spends it more efficiently than America. This is not done by impoverishing the physicians; British doctors are the second highest paid on the planet.
What I complain about in the NHS is the lack of freedom to individual clinicians. The bureaucrats have tried to turn medicine into painting by numbers. I once chaired an NHS committee that was trying to turn hematology into a protocol driven service that could be costed. They had done it for cholecystectomy, hernia repair and mastectomy. After 2 years of committee meetings I believe I had convinced them that it was impossible; patients were just too different. At least I convinced them that it was impossible with me as chairman, because the committee was disbanded, and I was never asked to chair another committee for the government.
The Conservative Party is holding its annual conference in Bournemouth this week. Their big new idea on health is 'Leave it to the professionals'.
Alleluia!
Servanthood
One of the blogs I regularly read is Ben Witherington. Today he has this parable.
The Holy Man and the Lord
A holy man was having a conversation with the Lord one day
and said, "Lord, I would like to know what Heaven and Hell are like."
The Lord led the holy man to two doors. He opened one of the doors and
the holy man looked in. In the middle of the room was a large round
table.
In the middle of the table was a large pot of stew which smelled
delicious and made the holy man's mouth water. The people sitting
round the table were thin and sickly.
They appeared to be famished. They were holding spoons with
very long handles that were strapped to their arms and each found it
possible to reach into the pot of stew and take a spoonful, but
because the handle was longer than their arms, they could not get the
spoons back into their mouths. The holy man shuddered at the sight of their
misery and suffering.
The Lord said, "You have seen Hell."
They went to the next room and opened the door. It was
exactly the same as the first one. There was the large round table with
the large pot of stew which made the holy man's mouth water.
The people were equipped with the same long-handled spoons,
but here the people were well nourished and plump, laughing and talking.
The holy man said, "I don't understand." "It is simple" said the Lord,
"it requires but one skill. You see, they have learned to feed each other, while the greedy think only of themselves."
It is a parable about servanthood. I thought about it while reading Brideshead Revisited. Many of my readers will be familiar with the story, either having read the book or seen the excellent television production that starred Anthony Andrews, Jeremy Irons, Clare Bloom, Diana Quick, Jeremy Sinden, John Gelguid and Laurence Olivier. But for those who don't remember, a brief synopsis: Charles Ryder, the narrator, is taken up, at the Oxford of the 1920s by Sebastian Flyte, a younger son of an impossibly rich English Lord. For two years at Oxford they are bosom chums (no they are not homosexual) living a dissolute life characterized by ever more drinking of fine wines. Charles is gradually seduced by Sebastian's family, a dysfunctional Catholic entity, where the parents are separated and the children idiosyncratic. Sebastian sees this as betrayal on Charles' part and sinks deeper and deeper into alcoholism.
Eventually we find Sebastian living in Tangiers in a terrible state. His alcoholism is far gone, but at last he has found a purpose in his life. He is living with a young German (no, they are not homosexuals). This young man is a useless wastrel, who shot himself in the foot to be invalided out of the French Foreign Legion. He has secondary syphilis. His foot will not heal. Sebastian acts as his servant. Although unwell himself, he struggles to fetch his cigarettes for him. He cleans and dresses the wound. He cares for him. "Someone has to be pretty bad to need me to help him," says Sebastian. Somehow in his degradation he has found the fulfillment that was missing amongst all the opulence.
Evelyn Waugh was a strange man; one of a string of English Catholic writers. Nowadays, it is rare for novelists even to bring God into the conversation, but Waugh wrote at a time when religion was real for most people. Catholics had a strong feeling of guilt. They might well be the greatest of sinners, but they couldn’t be comfortable in their sin. They knew that payment came later.
The Holy Man and the Lord
A holy man was having a conversation with the Lord one day
and said, "Lord, I would like to know what Heaven and Hell are like."
The Lord led the holy man to two doors. He opened one of the doors and
the holy man looked in. In the middle of the room was a large round
table.
In the middle of the table was a large pot of stew which smelled
delicious and made the holy man's mouth water. The people sitting
round the table were thin and sickly.
They appeared to be famished. They were holding spoons with
very long handles that were strapped to their arms and each found it
possible to reach into the pot of stew and take a spoonful, but
because the handle was longer than their arms, they could not get the
spoons back into their mouths. The holy man shuddered at the sight of their
misery and suffering.
The Lord said, "You have seen Hell."
They went to the next room and opened the door. It was
exactly the same as the first one. There was the large round table with
the large pot of stew which made the holy man's mouth water.
The people were equipped with the same long-handled spoons,
but here the people were well nourished and plump, laughing and talking.
The holy man said, "I don't understand." "It is simple" said the Lord,
"it requires but one skill. You see, they have learned to feed each other, while the greedy think only of themselves."
It is a parable about servanthood. I thought about it while reading Brideshead Revisited. Many of my readers will be familiar with the story, either having read the book or seen the excellent television production that starred Anthony Andrews, Jeremy Irons, Clare Bloom, Diana Quick, Jeremy Sinden, John Gelguid and Laurence Olivier. But for those who don't remember, a brief synopsis: Charles Ryder, the narrator, is taken up, at the Oxford of the 1920s by Sebastian Flyte, a younger son of an impossibly rich English Lord. For two years at Oxford they are bosom chums (no they are not homosexual) living a dissolute life characterized by ever more drinking of fine wines. Charles is gradually seduced by Sebastian's family, a dysfunctional Catholic entity, where the parents are separated and the children idiosyncratic. Sebastian sees this as betrayal on Charles' part and sinks deeper and deeper into alcoholism.
Eventually we find Sebastian living in Tangiers in a terrible state. His alcoholism is far gone, but at last he has found a purpose in his life. He is living with a young German (no, they are not homosexuals). This young man is a useless wastrel, who shot himself in the foot to be invalided out of the French Foreign Legion. He has secondary syphilis. His foot will not heal. Sebastian acts as his servant. Although unwell himself, he struggles to fetch his cigarettes for him. He cleans and dresses the wound. He cares for him. "Someone has to be pretty bad to need me to help him," says Sebastian. Somehow in his degradation he has found the fulfillment that was missing amongst all the opulence.
Evelyn Waugh was a strange man; one of a string of English Catholic writers. Nowadays, it is rare for novelists even to bring God into the conversation, but Waugh wrote at a time when religion was real for most people. Catholics had a strong feeling of guilt. They might well be the greatest of sinners, but they couldn’t be comfortable in their sin. They knew that payment came later.
Saturday, September 30, 2006

Friday, September 29, 2006
"Jesus is the slave of Allah"
One of the posters giving offence at a Muslim protest over the Pope's quotation said "Jesus is the slave of Allah". It was obviously designed as an insult and a declaration of the superiority of Islam over Christianity.
However, as I think about it, it exemplifies the superiority of Christianity over Islam as an approach to God.
I doubt that the poster bearer realizes it but the slogan derives from Paul's letter to the Philippians. "... Christ Jesus: who, being in the form of God, thought it not robbery to be equal with God: but made himself of no reputation and took upon him the form of a servant, and was made in the likeness of man." (Ch 2 vv 5-7). The Greek word translated 'servant' is 'doulos' and it should more properly be translated 'slave'. 'Allah' is, of course, simply the Arabic word for God.
It is true. Jesus is the slave of God. He was/is/always will be co-equal with God, but made himself a slave to demonstrate how to approach God.
Mohammed was a Catholic heretic. His new form of religion had a blind spot for humility and took upon itself the arrogance of conquest and subjection. Jesus taught that the first shall be last and the last first. Jesus taught that except you become as a little child you cannot enter the kingdom of heaven. Jesus taught that it is easier for a camel to go through the eye of a needle than a rich man to enter into the kingdom of heaven. Jesus taught that the poor in sprit, and the meek, and the peacemakers, and the merciful, and those who hunger and thirst after righteousness are blessed.
However, as I think about it, it exemplifies the superiority of Christianity over Islam as an approach to God.
I doubt that the poster bearer realizes it but the slogan derives from Paul's letter to the Philippians. "... Christ Jesus: who, being in the form of God, thought it not robbery to be equal with God: but made himself of no reputation and took upon him the form of a servant, and was made in the likeness of man." (Ch 2 vv 5-7). The Greek word translated 'servant' is 'doulos' and it should more properly be translated 'slave'. 'Allah' is, of course, simply the Arabic word for God.
It is true. Jesus is the slave of God. He was/is/always will be co-equal with God, but made himself a slave to demonstrate how to approach God.
Mohammed was a Catholic heretic. His new form of religion had a blind spot for humility and took upon itself the arrogance of conquest and subjection. Jesus taught that the first shall be last and the last first. Jesus taught that except you become as a little child you cannot enter the kingdom of heaven. Jesus taught that it is easier for a camel to go through the eye of a needle than a rich man to enter into the kingdom of heaven. Jesus taught that the poor in sprit, and the meek, and the peacemakers, and the merciful, and those who hunger and thirst after righteousness are blessed.
Thursday, September 28, 2006
Ruth Rendall
I have just finished Ruth Rendall's "Babes in the Wood". She is reputed to be one of the finest crime writers currently writing in England. Her detective, Inspector Wexford is a oldish policeman, who views the changes of modern life with a degree of irritation and dismay. He relies on his wife to work the Internet for him, and prefers books to television.
In this book, I particularly enjoyed two sentences.
"They have Moses and the prophets" says Wexford when he decides not to warn an ignorant character of the danger awaiting them.
I wondered how many readers would recognize that as a quote from Jesus' story of Lazarus and Dives.
"He performed a few tasks around the house making the beds and the coffee - now is that an example of zeugma, Giles?"
Giles grinned. 'No. It would be if you said, "making haste and the coffee". Yours is syllepsis.'
Now English grammar is one of my delights.
I enjoyed the book, though after James Elroy and Elmore Leonard it is a little parochial and cozy.
I have now started Brideshead and I know I am in for a treat.
In this book, I particularly enjoyed two sentences.
"They have Moses and the prophets" says Wexford when he decides not to warn an ignorant character of the danger awaiting them.
I wondered how many readers would recognize that as a quote from Jesus' story of Lazarus and Dives.
"He performed a few tasks around the house making the beds and the coffee - now is that an example of zeugma, Giles?"
Giles grinned. 'No. It would be if you said, "making haste and the coffee". Yours is syllepsis.'
Now English grammar is one of my delights.
I enjoyed the book, though after James Elroy and Elmore Leonard it is a little parochial and cozy.
I have now started Brideshead and I know I am in for a treat.
Tuesday, September 26, 2006
Blogging in Seattle
My son, now in Seattle, has started a blog. If you want to share in his culture shock start reading here.
Splenic marginal zone lymphoma (SMZL)
SMZL is one of the diseases that get misdiagnosed as CLL. Before we had flow cytometry there was some excuse for this, but increasingly it is an error that oncologists ought to know about.
I remember attending a meeting at a country house near Windsor in the 1980s. All the great CLL names were there: Binet, Rai, Catovsky, Montserrat, Caligaris-Cappio, Galton, Hansen, Kimby and many others. The French group was talking about a group of cases that they staged as A2, who had a very good prognosis. This meant that they had enlarged spleens but no lymph nodes to feel. We now know that these were cases of SMZL.
David Oscier joined me in Bournemouth in 1981. One of the first things he did was to set about establishing a center of excellence for CLL cytogenetics. It was he who discovered the 13q deletion in CLL. Among the things that he discovered were a group of patients who despite having a complex karyotype, often involving the long arm of chromosome 7, were very benign. In retrospect, these patients had SMZL.
I remember one patient whose name was the same as a famous poet from World War One, who had both CLL and sideroblastic anemia. His lymphocytes were rather large and angry looking, even having small 'hairs' at one end. Despite this his disease was entirely benign. Another patient, a woman who had been with me for many years, has some odd features. She had a monoclonal protein in her serum. She responded quite well to chlorambucil, but she developed a bad case of shingles, affecting the skin of the back of the leg, but, most unusually, also affecting the muscles, a case of the very rare 'motor shingles'. She is the only patient I have seen to have developed acute myeloid leukemia after treatment with chlorambucil. Another patient I remember also had a small monoclonal protein in his serum, but as a consequence developed intermittent attacks of abdominal pain and swelling of the lips and mouth so as to interfere with his breathing. Despite having the protein that acts as an inhibitor or C1 esterase, he had no C1 esterase activity in his blood. In retrospect, all three of these patients had SMZL.
SMZL, then, is a condition that mimics CLL but one that has important differences.
The WHO classification recognizes three types of marginal zone lymphoma: Extranodal marginal zone lymphoma (which occurs in the mucosa associated lymphoid tissue [MALT lymphomas] such as occur in the stomach and are often associated with helicobacter pylori), Nodal marginal zone lymphoma (sometimes called monocytoid B cell lymphoma) and SMZL. We can ignore the other two, which simply confuse matters. SMZL was not differentiated from CLL in previous classifications.
In some cases of SMZL the lymphocytes have small hairs or 'villi' sticking out from the surface, especially at one and of the cell, which was why some people call it splenic lymphoma with villous lymphocytes (SLVL), but these are not always seen, even in the same case on different occasions, which is why I prefer the SMZL name.
The hairs are the cause of the resemblance to hairy cell leukemia, but in real life they are so different that nobody should confuse them. The SMZL cells are rather larger than CLL cells and have obviously more cytoplasm
The biggest distinction between CLL and SMZL is CD5. Anything that seems to be CLL yet is CD5 negative is likely to be SMZL.
SMZL is a lymphoma of small lymphocytes that seems to arise in the spleen. They replace the splenic white pulp germinal centers, wipe out the follicular mantle, and merge with the marginal zone of larger cells, which include some larger blast-like cells. Both small and large cells invade the red pulp and the lymph nodes at the hilum of the spleen are involved. The bone marrow and blood are also usually involved, but the lymph nodes only very rarely.
SMZL is quite rare, comprising about 1% of lymphomas. It usually presents with an enlarged spleen , or as an incidental finding of a high white count. About a third of patients have a monoclonal immunoglobulin in the blood and this has led some people to think that it overlaps with Waldenstrom's macroglobulinemia, but the monoclonal protein is never very high so as to cause hyperviscosity, nor does it usually cause hypogammaglobulinemia by depressing the normal immunoglobulins.
The immunophenotype is CD19+, CD20+, surface Ig bright, CD79b+, but CD5 neg, CD23 neg, CD43 neg.
The chromosomes are abnormal in more than half of cases with deletion of the long arm of chromosome 7 missing in about 40%. the deletion is between 7q21-32 and is thought to involve the CDK6 gene. Occasional the t(11;14) translocation has been reported, but these cases seem to be cases of mantle cell lymphoma that have been misdiagnosed.
Most cases have mutated IgVH genes, though occasional unmutated cases have been reported. There are some suggestions that this may be a prognostic factor in SMZL, just as it is in CLL. But the prognosis is usually much better than in CLL, with most cases being very indolent. Anemia or thrombocytopenia when they occur are often caused by hypersplenism (an overactive spleen) and are best treated by splenectomy. In retrospect, the first case of this condition that I saw was in 1969. An old woman with lymphoma was apparently cured by splenectomy.
So, the first thing you do with SMZL is get the diagnosis right because it is so error prone. The second thing is to watch and wait. If treatment becomes necessary then splenectomy is first choice. Chemotherapy comes bottom of the list, but the type of chemotherapy to use is not evidence based, and most people would follow the same practice that they use in CLL.
Complications of SMZL include a Richter-like transformation and acquired angioedema.
I remember attending a meeting at a country house near Windsor in the 1980s. All the great CLL names were there: Binet, Rai, Catovsky, Montserrat, Caligaris-Cappio, Galton, Hansen, Kimby and many others. The French group was talking about a group of cases that they staged as A2, who had a very good prognosis. This meant that they had enlarged spleens but no lymph nodes to feel. We now know that these were cases of SMZL.
David Oscier joined me in Bournemouth in 1981. One of the first things he did was to set about establishing a center of excellence for CLL cytogenetics. It was he who discovered the 13q deletion in CLL. Among the things that he discovered were a group of patients who despite having a complex karyotype, often involving the long arm of chromosome 7, were very benign. In retrospect, these patients had SMZL.
I remember one patient whose name was the same as a famous poet from World War One, who had both CLL and sideroblastic anemia. His lymphocytes were rather large and angry looking, even having small 'hairs' at one end. Despite this his disease was entirely benign. Another patient, a woman who had been with me for many years, has some odd features. She had a monoclonal protein in her serum. She responded quite well to chlorambucil, but she developed a bad case of shingles, affecting the skin of the back of the leg, but, most unusually, also affecting the muscles, a case of the very rare 'motor shingles'. She is the only patient I have seen to have developed acute myeloid leukemia after treatment with chlorambucil. Another patient I remember also had a small monoclonal protein in his serum, but as a consequence developed intermittent attacks of abdominal pain and swelling of the lips and mouth so as to interfere with his breathing. Despite having the protein that acts as an inhibitor or C1 esterase, he had no C1 esterase activity in his blood. In retrospect, all three of these patients had SMZL.
SMZL, then, is a condition that mimics CLL but one that has important differences.
The WHO classification recognizes three types of marginal zone lymphoma: Extranodal marginal zone lymphoma (which occurs in the mucosa associated lymphoid tissue [MALT lymphomas] such as occur in the stomach and are often associated with helicobacter pylori), Nodal marginal zone lymphoma (sometimes called monocytoid B cell lymphoma) and SMZL. We can ignore the other two, which simply confuse matters. SMZL was not differentiated from CLL in previous classifications.
In some cases of SMZL the lymphocytes have small hairs or 'villi' sticking out from the surface, especially at one and of the cell, which was why some people call it splenic lymphoma with villous lymphocytes (SLVL), but these are not always seen, even in the same case on different occasions, which is why I prefer the SMZL name.
The hairs are the cause of the resemblance to hairy cell leukemia, but in real life they are so different that nobody should confuse them. The SMZL cells are rather larger than CLL cells and have obviously more cytoplasm
The biggest distinction between CLL and SMZL is CD5. Anything that seems to be CLL yet is CD5 negative is likely to be SMZL.
SMZL is a lymphoma of small lymphocytes that seems to arise in the spleen. They replace the splenic white pulp germinal centers, wipe out the follicular mantle, and merge with the marginal zone of larger cells, which include some larger blast-like cells. Both small and large cells invade the red pulp and the lymph nodes at the hilum of the spleen are involved. The bone marrow and blood are also usually involved, but the lymph nodes only very rarely.
SMZL is quite rare, comprising about 1% of lymphomas. It usually presents with an enlarged spleen , or as an incidental finding of a high white count. About a third of patients have a monoclonal immunoglobulin in the blood and this has led some people to think that it overlaps with Waldenstrom's macroglobulinemia, but the monoclonal protein is never very high so as to cause hyperviscosity, nor does it usually cause hypogammaglobulinemia by depressing the normal immunoglobulins.
The immunophenotype is CD19+, CD20+, surface Ig bright, CD79b+, but CD5 neg, CD23 neg, CD43 neg.
The chromosomes are abnormal in more than half of cases with deletion of the long arm of chromosome 7 missing in about 40%. the deletion is between 7q21-32 and is thought to involve the CDK6 gene. Occasional the t(11;14) translocation has been reported, but these cases seem to be cases of mantle cell lymphoma that have been misdiagnosed.
Most cases have mutated IgVH genes, though occasional unmutated cases have been reported. There are some suggestions that this may be a prognostic factor in SMZL, just as it is in CLL. But the prognosis is usually much better than in CLL, with most cases being very indolent. Anemia or thrombocytopenia when they occur are often caused by hypersplenism (an overactive spleen) and are best treated by splenectomy. In retrospect, the first case of this condition that I saw was in 1969. An old woman with lymphoma was apparently cured by splenectomy.
So, the first thing you do with SMZL is get the diagnosis right because it is so error prone. The second thing is to watch and wait. If treatment becomes necessary then splenectomy is first choice. Chemotherapy comes bottom of the list, but the type of chemotherapy to use is not evidence based, and most people would follow the same practice that they use in CLL.
Complications of SMZL include a Richter-like transformation and acquired angioedema.
Monday, September 25, 2006
Vienna
I have just returned after a few days in Vienna attending an educational meeting. It was organized by Oncology Network Europe. The format consists of 8 difficult Hematology cases presented by the discussion leader. The audience then responds to a series of multiple choice questions on how they would manage the cases. After this an international expert gives a short talk, reviewing the published evidence for various management strategies.
The topics covered were imatanib resistant CML, rituximab resistant follicular lymphoma, the 5q minus syndrome, early management of myeloma, late management of myeloma, iron overload in MDS, 17p deleted CLL, and the use of rituximab in induction and maintenance in follicular lymphoma.
The first thing to say is that there were absolutely no queues at Heathrow. I walked straight to the Austrian Airlines check in, and had the choice of two attendants. I have never been through security so quickly. They are obviously employing more staff to do the checks. Transfer from the airport to the city is by rapid train that takes 16 minutes and runs every 30 minutes, 24/7/365. I stayed at the Marriott, which was excellent and a short walk through the park from the train station.
The meeting was excellent. I am surprised at how few attended. If any hematologist in Europe is reading this I urge them to go to the next one. There are no catches.
Vienna (or Wien as the locals call it - why don't we stick to the English names of Bombay and Burma? We don't talk about Paree or Milano or Firenze? More PC nonsense, of course. Has anyone got a Beijinese dog?), Vienna is a beautiful city. There are many buildings on the grand scale, as befits what once the capital of a vast empire. Now that Austria is a minor country in the EU, it all seems a bit over scale, but no less beautiful. What I noticed was the absence of security. No concrete barriers to deter car bombs. No searches to protect against suicide bombers. It was if the German speaking community felt safe, here in their heartland.
Sitting beside me on the plane was a young woman about the age of my eldest daughter. She had been awarded an honor in the Queen's birthday honors list. She had an MBE for services to charity. She was of Greek extraction and ran a property development company; old buildings made fit for luxury living. She had been chairman of a local Conservative association and she was a lawyer. I think she had some sort of role as a minor judge, and certainly sat as a magistrate. She was adamant that Eastern Europeans from the recent EU entrants were responsible for most of the crime in north London and she didn't have a good word to say about Muslims.
She said that honors depended on who nominated you and how the nomination was phrased. Strange, I thought you applied for one and paid over your cash. Yes, I know that sounds cynical, but when you see who gets them and, more to the point, who doesn’t, you begin to be suspicious about the whole system.
With a little spare time in Vienna I decided to listen to some music. Being the 250th Mozart anniversary made the choice easy. There were numerous Mozart and Strauss concerts, but teh choice of music was rather hackneyed. All featured Eine Kleine Nachtmusik and the Beautiful Blue Danube, as well as overture from Figaro.
Eventually I settled on a chamber concert at Mozart's house (actually he lived tere for a couple of months, though Brahms lived there for a couple of years, no doubt hoping that some of the magic would rub off).
As well as the ubiquitous K.V.525 we have the Divertimento in D sharp K.V. 136, which most people would recognize and the Dissonanzen Quartett K.V. 465 which most people would not. The room was lavishly decorated with nubile cherubs and had very good acoustics for teh 35 in the audiance who packed the small room.
The topics covered were imatanib resistant CML, rituximab resistant follicular lymphoma, the 5q minus syndrome, early management of myeloma, late management of myeloma, iron overload in MDS, 17p deleted CLL, and the use of rituximab in induction and maintenance in follicular lymphoma.
The first thing to say is that there were absolutely no queues at Heathrow. I walked straight to the Austrian Airlines check in, and had the choice of two attendants. I have never been through security so quickly. They are obviously employing more staff to do the checks. Transfer from the airport to the city is by rapid train that takes 16 minutes and runs every 30 minutes, 24/7/365. I stayed at the Marriott, which was excellent and a short walk through the park from the train station.
The meeting was excellent. I am surprised at how few attended. If any hematologist in Europe is reading this I urge them to go to the next one. There are no catches.
Vienna (or Wien as the locals call it - why don't we stick to the English names of Bombay and Burma? We don't talk about Paree or Milano or Firenze? More PC nonsense, of course. Has anyone got a Beijinese dog?), Vienna is a beautiful city. There are many buildings on the grand scale, as befits what once the capital of a vast empire. Now that Austria is a minor country in the EU, it all seems a bit over scale, but no less beautiful. What I noticed was the absence of security. No concrete barriers to deter car bombs. No searches to protect against suicide bombers. It was if the German speaking community felt safe, here in their heartland.
Sitting beside me on the plane was a young woman about the age of my eldest daughter. She had been awarded an honor in the Queen's birthday honors list. She had an MBE for services to charity. She was of Greek extraction and ran a property development company; old buildings made fit for luxury living. She had been chairman of a local Conservative association and she was a lawyer. I think she had some sort of role as a minor judge, and certainly sat as a magistrate. She was adamant that Eastern Europeans from the recent EU entrants were responsible for most of the crime in north London and she didn't have a good word to say about Muslims.
She said that honors depended on who nominated you and how the nomination was phrased. Strange, I thought you applied for one and paid over your cash. Yes, I know that sounds cynical, but when you see who gets them and, more to the point, who doesn’t, you begin to be suspicious about the whole system.
With a little spare time in Vienna I decided to listen to some music. Being the 250th Mozart anniversary made the choice easy. There were numerous Mozart and Strauss concerts, but teh choice of music was rather hackneyed. All featured Eine Kleine Nachtmusik and the Beautiful Blue Danube, as well as overture from Figaro.
Eventually I settled on a chamber concert at Mozart's house (actually he lived tere for a couple of months, though Brahms lived there for a couple of years, no doubt hoping that some of the magic would rub off).
As well as the ubiquitous K.V.525 we have the Divertimento in D sharp K.V. 136, which most people would recognize and the Dissonanzen Quartett K.V. 465 which most people would not. The room was lavishly decorated with nubile cherubs and had very good acoustics for teh 35 in the audiance who packed the small room.
Wednesday, September 20, 2006
Bungs
It is almost two years since Brian Clough died. Brian was asked once whether he was the greatest football manager ever. "I wouldn't say that," he replied, "but I'd be on a short list of one."
He was a remarkable character. He played center forward for Middlesborough, scoring over 30 goals a season until he retire young having torn his anterior cruciate ligament. I did mine at about the same time, and in those days there was no operation to repair it. He went into football management, first with Hartlepool in the lower divisions and then with Derby County and Nottingham Forrest, both teams in the Midlands that would find it hard to make the first division. He won championships with both, but his great achievement was to win the European cup twice with Notts Forrest. Up there with teams like Inter Milan, Juventus, Barcelona and Real Madrid. He was very self opinionated, rude to the press, and big-headed. He has been known to strike young fans whom he thought were behaving disrespectfully to their elders. He was a drinker who needed a liver transplant.
It was said of him that he liked a bung. A bung is nothing to do with beer barrels. It is a sum of money taken as a bribe to facilitate a transfer from one club to another. These transfers fetch a huge amount of money. Nowadays it may be as much as $50 million. The player's agent takes a cut of the transfer fee, and he may pay an illicit amount to one or other of the club managers.
This week bungs are in the news again. A BBC investigation has suggested that as many as 8 of the First Division managers are up for a bung. When it came down to it, the investigation was rather short on naming names. Most prominent was Sam Allardyce, the manager of Bolton Wanderers. He has a reputation of building a team from other manager's cast-offs. Of course he denies everything and what usually happens in cases like this is that there is not enough evidence to nail anybody.
Unexpectedly exonerated was Harry Redknapp. At one time manager of Bournemouth, Harry has moved around a bit, to West Ham, to Portsmouth, to Southampton and back to Portsmouth again. Currently, Portsmouth are top of the top division. He is more active in the transfer market than anyone and regularly takes players that nobody else could cope with. Because of his transfer activity and the size of his house (he lives in the most salubrious part of Bournemouth where houses often sell for more than $10 million) people think that he must be on the fiddle, but perhaps this is just his severance pay from all the jobs he has been sacked from. He also believed to be a bit of a gambler, so perhaps he studies form. Anyway, the investigation couldn't lay a glove on Harry.
I'm rather glad. I have a soft spot for Harry, East End wide boy that he is. His son went to school with my boy (Christian Bale, the actor, was there at the same time) when I was a school governor.
He was a remarkable character. He played center forward for Middlesborough, scoring over 30 goals a season until he retire young having torn his anterior cruciate ligament. I did mine at about the same time, and in those days there was no operation to repair it. He went into football management, first with Hartlepool in the lower divisions and then with Derby County and Nottingham Forrest, both teams in the Midlands that would find it hard to make the first division. He won championships with both, but his great achievement was to win the European cup twice with Notts Forrest. Up there with teams like Inter Milan, Juventus, Barcelona and Real Madrid. He was very self opinionated, rude to the press, and big-headed. He has been known to strike young fans whom he thought were behaving disrespectfully to their elders. He was a drinker who needed a liver transplant.
It was said of him that he liked a bung. A bung is nothing to do with beer barrels. It is a sum of money taken as a bribe to facilitate a transfer from one club to another. These transfers fetch a huge amount of money. Nowadays it may be as much as $50 million. The player's agent takes a cut of the transfer fee, and he may pay an illicit amount to one or other of the club managers.
This week bungs are in the news again. A BBC investigation has suggested that as many as 8 of the First Division managers are up for a bung. When it came down to it, the investigation was rather short on naming names. Most prominent was Sam Allardyce, the manager of Bolton Wanderers. He has a reputation of building a team from other manager's cast-offs. Of course he denies everything and what usually happens in cases like this is that there is not enough evidence to nail anybody.
Unexpectedly exonerated was Harry Redknapp. At one time manager of Bournemouth, Harry has moved around a bit, to West Ham, to Portsmouth, to Southampton and back to Portsmouth again. Currently, Portsmouth are top of the top division. He is more active in the transfer market than anyone and regularly takes players that nobody else could cope with. Because of his transfer activity and the size of his house (he lives in the most salubrious part of Bournemouth where houses often sell for more than $10 million) people think that he must be on the fiddle, but perhaps this is just his severance pay from all the jobs he has been sacked from. He also believed to be a bit of a gambler, so perhaps he studies form. Anyway, the investigation couldn't lay a glove on Harry.
I'm rather glad. I have a soft spot for Harry, East End wide boy that he is. His son went to school with my boy (Christian Bale, the actor, was there at the same time) when I was a school governor.
Tuesday, September 19, 2006
Hard times
There are periods in one's life when a succession of set backs sends one reeling. This is one such time for me and my family. I have written about my father-in-law, but that was only the start. Some things are too personal to write about. This is addressed to those of my readers who pray. Please, pray for us now.
Monday, September 18, 2006
Sky Captain and the World of Tomorrow
If you get a chance to watch this movie, avoid it like the plague. What utter tosh!
Sunday, September 17, 2006
Reaction to the Pope's speech
The riots in response to the Pope's suggestion that Islam is not a rational religion put me in mind of another riot that took place against Christianity, in Ephesus.
Paul and his colleagues had been so successful in his evangelism that the metalworkers whose livelihood came from crafting idols were being hit in the pocket. They fomented a riot that led to the intervention of the city clerk.
This was the clerk’s judgment. "You have brought these men here, though they have neither robbed temples, nor blasphemed our goddess (Artemis or Diana). If Demetrius and his fellow craftsmen have a grievance against anybody, the courts are open and there are proconsuls. They can press charges. If there is anything further you want to bring up, it must be settled in a legal assembly. As it is we are in danger of being charged with rioting because of today's events. In that case we would not be able to account for this commotion, since there is no reason for it." (Acts 19:37-40)
If the Pope's message was offensive to Muslim's their reaction seems to justify his charge. He says there is no reason in Islam and its adherents respond irrationally.
This is unfair, of course, since adherent of all religions, Christianity not excluded, are prone to act irrationally if they feel their cherished beliefs are threatened. Usually there is a calming voice, like the city clerk in Ephesus, who will point out the lack of wisdom in such a response. Where is the calming voice among Muslims?
It is interesting to see what Paul was preaching about that so raised the ire of the Ephesians. We can get a flavor of Paul's message from what he had been preaching in Corinth. In Acts ch 18 v5 we read, "Paul devoted himself exclusively to preaching, testifying to the Jews that Jesus was the Messiah." In his letter to the Corinthian church, he testifies, "I determined to know nothing while I was with you except Jesus Christ and him crucified." (I Cor 2:2). In addition the first chapter of the letter to the Ephesians spells out that message in full.
The point that I am making is that rather than insulting the local religion, Paul preaches the merits of Christ. In Athens, he makes use of the Greek’s polytheism and superstition by centering his remarks on the alter to “an unknown god”.
We would do well to remember that Muslims are part of the “all nations” for whom we were given the great commission. They are among the sinners who are called to repentance. There is one remedy for sin, whether you are Jew, Muslim or Christian. We should not waste time denigrating the beliefs of others. We should, like Paul, devote ourselves to preaching Jesus Christ and him crucified.
Paul and his colleagues had been so successful in his evangelism that the metalworkers whose livelihood came from crafting idols were being hit in the pocket. They fomented a riot that led to the intervention of the city clerk.
This was the clerk’s judgment. "You have brought these men here, though they have neither robbed temples, nor blasphemed our goddess (Artemis or Diana). If Demetrius and his fellow craftsmen have a grievance against anybody, the courts are open and there are proconsuls. They can press charges. If there is anything further you want to bring up, it must be settled in a legal assembly. As it is we are in danger of being charged with rioting because of today's events. In that case we would not be able to account for this commotion, since there is no reason for it." (Acts 19:37-40)
If the Pope's message was offensive to Muslim's their reaction seems to justify his charge. He says there is no reason in Islam and its adherents respond irrationally.
This is unfair, of course, since adherent of all religions, Christianity not excluded, are prone to act irrationally if they feel their cherished beliefs are threatened. Usually there is a calming voice, like the city clerk in Ephesus, who will point out the lack of wisdom in such a response. Where is the calming voice among Muslims?
It is interesting to see what Paul was preaching about that so raised the ire of the Ephesians. We can get a flavor of Paul's message from what he had been preaching in Corinth. In Acts ch 18 v5 we read, "Paul devoted himself exclusively to preaching, testifying to the Jews that Jesus was the Messiah." In his letter to the Corinthian church, he testifies, "I determined to know nothing while I was with you except Jesus Christ and him crucified." (I Cor 2:2). In addition the first chapter of the letter to the Ephesians spells out that message in full.
The point that I am making is that rather than insulting the local religion, Paul preaches the merits of Christ. In Athens, he makes use of the Greek’s polytheism and superstition by centering his remarks on the alter to “an unknown god”.
We would do well to remember that Muslims are part of the “all nations” for whom we were given the great commission. They are among the sinners who are called to repentance. There is one remedy for sin, whether you are Jew, Muslim or Christian. We should not waste time denigrating the beliefs of others. We should, like Paul, devote ourselves to preaching Jesus Christ and him crucified.
Saturday, September 16, 2006
Publishing is theft.
I have just read an interesting article by Richard Smith, ex-editor of the British Medical Journal, on the theme that publishing is theft. The idea is that the publishers make millions from publishing scientific journals, but their imput is minor.
The articles that they publish cost them nothing, the research is funded from public funds, or charity, or the pharamceutical industry. The journal has to pay to register the article, but the editorial assisatnts who do this are among the poorly paid. The editor nowadays is paid (unless he works for one of the many societies that publish scientific journals - these editors are largely unpaid) but the amount he is paid is nowhere near the market rate. He is often a leading academic who may gather prestige from editing a major journal, but prestige don't pay the rent.
Then the paper is sent to referees who are unpaid. Refereeing is hard work and anonylous, so no-one gets any prestige for that. It is seen as a professional duty. You want your papers refereed so you must referee other people's.
Finally the paper goes back to the publisher who must pay for the setting (cheaper now it is electronic) and proofing and printing. This may not cost much at all, many journals have a print run of about 500 copies only. Marketing needs to be done, but this is often rudimentary. These journals are must-haves for the scientific community and libraries are bound to buy them. The price is inflated. A year's subscription to Brain Research costs about the same as a medium sized automobile.
As an Author, Editor and a Reviewer I find much to agree with in this article, though the alternative - PUBMED - imposes charges on the author which will deter the individual without a large research grant behind him from publishing at all.
Today I refereed two papers for a hematology journal with an impact factor of over 3. They were dreadful. Almost insulting that the authors tried to get them published. Undoubtedly they will turn up somewhere in a journal short of copy. I will keep my eyes open for them.
Also today I read an article about a clinical trial of a supposed cure for the common cold published in The Lancet in 1944. It was of course useless, even though it had reviously been lauded in a British newspaper, The Sunday Express. Somebody said about that newspaper that the only things you could believe that was written in it were the title, the date and the price.
Typically, the product is still being marketed in Brazil, but you can get it over the Internet.
The articles that they publish cost them nothing, the research is funded from public funds, or charity, or the pharamceutical industry. The journal has to pay to register the article, but the editorial assisatnts who do this are among the poorly paid. The editor nowadays is paid (unless he works for one of the many societies that publish scientific journals - these editors are largely unpaid) but the amount he is paid is nowhere near the market rate. He is often a leading academic who may gather prestige from editing a major journal, but prestige don't pay the rent.
Then the paper is sent to referees who are unpaid. Refereeing is hard work and anonylous, so no-one gets any prestige for that. It is seen as a professional duty. You want your papers refereed so you must referee other people's.
Finally the paper goes back to the publisher who must pay for the setting (cheaper now it is electronic) and proofing and printing. This may not cost much at all, many journals have a print run of about 500 copies only. Marketing needs to be done, but this is often rudimentary. These journals are must-haves for the scientific community and libraries are bound to buy them. The price is inflated. A year's subscription to Brain Research costs about the same as a medium sized automobile.
As an Author, Editor and a Reviewer I find much to agree with in this article, though the alternative - PUBMED - imposes charges on the author which will deter the individual without a large research grant behind him from publishing at all.
Today I refereed two papers for a hematology journal with an impact factor of over 3. They were dreadful. Almost insulting that the authors tried to get them published. Undoubtedly they will turn up somewhere in a journal short of copy. I will keep my eyes open for them.
Also today I read an article about a clinical trial of a supposed cure for the common cold published in The Lancet in 1944. It was of course useless, even though it had reviously been lauded in a British newspaper, The Sunday Express. Somebody said about that newspaper that the only things you could believe that was written in it were the title, the date and the price.
Typically, the product is still being marketed in Brazil, but you can get it over the Internet.
Friday, September 15, 2006
Dogville
Last night I watched the film Dogville. It is an unusual production, more like theater than film, with much left to the imagination. It addressed the problem of human responsibility.
A scorpion asks a frog to transport it across a river. The frog demurs fearing the scorpion will sting it. “Why would I sting you? We would both drown.”
Convinced by the argument the frog agrees. Half way across the scorpion stings the frog. “Why did you do that?” asks the frog, “Now we will both drown.”
“I could not help it,” replies the scorpion, “it is in my nature.”
The film approaches just this question. Should we excuse immoral behavior because of extenuating situations like poverty, poor education, family background and the rest? Is an attitude of stoicism, where we suffer other people’s bad behavior because they know no better the best approach?
In the end the film answers with a resounding, “No!”
People should behave better. If they do not they must take responsibility for their actions.
It is a very right wing movie.
A scorpion asks a frog to transport it across a river. The frog demurs fearing the scorpion will sting it. “Why would I sting you? We would both drown.”
Convinced by the argument the frog agrees. Half way across the scorpion stings the frog. “Why did you do that?” asks the frog, “Now we will both drown.”
“I could not help it,” replies the scorpion, “it is in my nature.”
The film approaches just this question. Should we excuse immoral behavior because of extenuating situations like poverty, poor education, family background and the rest? Is an attitude of stoicism, where we suffer other people’s bad behavior because they know no better the best approach?
In the end the film answers with a resounding, “No!”
People should behave better. If they do not they must take responsibility for their actions.
It is a very right wing movie.
Thursday, September 14, 2006
Weight loss in CLL
One of the criteria for treatment of CLL is weight loss. The criterion has been lifted straight from the criteria identified for the Ann Arbor staging of Hodgkin's disease that advance the stage from A to B. Weight loss of greater than 10% body weight over 6 months, fever and night sweats were included, while other systemic characteristics like alcohol induced pain, itching and rash were not. The criteria for Hodgkins's disease date from the 1971, at a time when we did not have CT scanning for abdominal glands.
Patients with apparent stage 0 or 1 CLL might have these systemic symptoms yet appear to have low bulk disease. CT scanning usually reveals that they have lymph nodes at the back of the abdomen that cannot be felt with the hand. This is particularly common in younger men who have the 11q deletion.
But it is important to realize that systemic symptoms like this may have causes other than CLL. Weight loss occurs with thyrotoxicosis (an over active thyroid gland), with malabsorption, with anorexia, and of course in many systemic illnesses like TB and other chronic infections. It also occurs with old age. Aging reduces muscle bulk. Muscles need constant exercise to keep their size, and the relative immobility of the old means that they lose weight. Sometimes anabolic steroids (the kind that atheletes use illegaly are given to old people to prevent this.
As I see it, systemic symptoms in low stage CLL should be an indication for investigation. This almost certainly should include a CT scan. They should not be regarded as a sole indication for treatment, unless there are other indications of progression. For one thing it would be foolhardy to give cytotoxic drugs to someone with occult TB.
Cacchexin is the old name for tumor necrosis factor (TNF). It causes, among other things, cacchexia (the wasting condition associated with cancer). TNF is made by CLL cells so it is hardly surprising that weight loss should occur in CLL, but I can't remember a single patient in my experience where this was the sole indication for treatment.
Patients with apparent stage 0 or 1 CLL might have these systemic symptoms yet appear to have low bulk disease. CT scanning usually reveals that they have lymph nodes at the back of the abdomen that cannot be felt with the hand. This is particularly common in younger men who have the 11q deletion.
But it is important to realize that systemic symptoms like this may have causes other than CLL. Weight loss occurs with thyrotoxicosis (an over active thyroid gland), with malabsorption, with anorexia, and of course in many systemic illnesses like TB and other chronic infections. It also occurs with old age. Aging reduces muscle bulk. Muscles need constant exercise to keep their size, and the relative immobility of the old means that they lose weight. Sometimes anabolic steroids (the kind that atheletes use illegaly are given to old people to prevent this.
As I see it, systemic symptoms in low stage CLL should be an indication for investigation. This almost certainly should include a CT scan. They should not be regarded as a sole indication for treatment, unless there are other indications of progression. For one thing it would be foolhardy to give cytotoxic drugs to someone with occult TB.
Cacchexin is the old name for tumor necrosis factor (TNF). It causes, among other things, cacchexia (the wasting condition associated with cancer). TNF is made by CLL cells so it is hardly surprising that weight loss should occur in CLL, but I can't remember a single patient in my experience where this was the sole indication for treatment.
Tuesday, September 12, 2006
Are we losing the war?
Are we losing the war? It seems incomprehensible that the huge armies of the west with their advanced military equipment should be defeated by a bunch of tribesmen with rifles. But wars are not fought like that any more.
The other night I watched Alan Parkers's movie "Michael Collins". Seeing the massacre at the Dublin Post Office in 1916, Collins conceived the idea of asymmetric warfare. The IRA would not wear uniforms. They would merge with the indigenous people. They would put spies in police headquarters. They would thrive on good intelligence.
It worked well until Devalera returned and insisted on a conventional confrontation. This reduced the power of the IRA so that they would have had difficulty in surviving another week. Fortunately for them, the British government offered a truce and a settlement - the Irish Free State and partition in the north - was agreed.
The same asymmetric tactics were adopted by the Provisional IRA in the 1970s. Again counter-intelligence measures brought the Provos close to defeat and they accepted a truce. All they got was an amnesty. Ireland is still partitioned. Despite the failure of the new Northern Ireland Assembly we do not see a return to bombing and kidnap. The world has moved on a notch. The biggest change is that the people of Ireland are wealthier now. They have nothing to complain about. The stiffness of fundamentalist Catholicism has been shaken off and an emancipated people have taken to enterprise.
But we know how to defeat that sort of terrorism. You do not bombard Belfast with shock and awe. You need to infiltrate the enemy. You must have good intelligence. You must isolate the terrorist from his community. You win by thinking, not by violent reaction. Eventually the terrorist has to talk, and he will, for although he will have many foot soldiers willing to commit suicide, the generals do not think in the same way.
The most effective counter insurgency campaign was fought by the British in Malaya. It worked by keeping the villages segregated from the terrorist.
Asymmetric warfare has been adopted in many theaters of war. From Vietnam to Iraq powerful armies have been tied down by booby traps, roadside bombs, suicide bombers, train bombs and the rest. Had Hitler invaded Britain in 1940, Churchill had plans to lead a guerilla war on English soil.
The guerilla operates from cells. Adjacent cells do not know each other. Funding is easy via the internet, and besides guerilla warfare is not expensive. The local community is loyal because it is cultivated. Both Hamas and Hezbollah see themselves as social benefactors for their communities, but there are punishment beatings for those who step out of line. Indoctrination is a usual device. Whether it is readings from Marx or the Koran, it is necessary to commit your own side to one world view.
The media are the most important arm of the terrorist. I don't think that Western governments have caught on to this yet. We proudly display our independent, uncensored media, but the enemy has no such compunctions. They say, "Telling a lie is not a sin if it helps our side this war to win." The enemy has infiltrated our mainstream media. Try to discover how many at the BBC are Muslim converts. The American media lost America the Viet Nam war. The Somalia debacle and the Beirut bomb were designed to play on American television. In Iraq and Afghanistan the media are playing the same "troops out" card. Governments must be much smarter at using the media.
Are we losing the war? Not yet, but we are not winning it. We need some thinkers on duty. I have been listening to a few military strategists over the last few days. I have become convinced that at last we are putting some good minds on the problem.
The other night I watched Alan Parkers's movie "Michael Collins". Seeing the massacre at the Dublin Post Office in 1916, Collins conceived the idea of asymmetric warfare. The IRA would not wear uniforms. They would merge with the indigenous people. They would put spies in police headquarters. They would thrive on good intelligence.
It worked well until Devalera returned and insisted on a conventional confrontation. This reduced the power of the IRA so that they would have had difficulty in surviving another week. Fortunately for them, the British government offered a truce and a settlement - the Irish Free State and partition in the north - was agreed.
The same asymmetric tactics were adopted by the Provisional IRA in the 1970s. Again counter-intelligence measures brought the Provos close to defeat and they accepted a truce. All they got was an amnesty. Ireland is still partitioned. Despite the failure of the new Northern Ireland Assembly we do not see a return to bombing and kidnap. The world has moved on a notch. The biggest change is that the people of Ireland are wealthier now. They have nothing to complain about. The stiffness of fundamentalist Catholicism has been shaken off and an emancipated people have taken to enterprise.
But we know how to defeat that sort of terrorism. You do not bombard Belfast with shock and awe. You need to infiltrate the enemy. You must have good intelligence. You must isolate the terrorist from his community. You win by thinking, not by violent reaction. Eventually the terrorist has to talk, and he will, for although he will have many foot soldiers willing to commit suicide, the generals do not think in the same way.
The most effective counter insurgency campaign was fought by the British in Malaya. It worked by keeping the villages segregated from the terrorist.
Asymmetric warfare has been adopted in many theaters of war. From Vietnam to Iraq powerful armies have been tied down by booby traps, roadside bombs, suicide bombers, train bombs and the rest. Had Hitler invaded Britain in 1940, Churchill had plans to lead a guerilla war on English soil.
The guerilla operates from cells. Adjacent cells do not know each other. Funding is easy via the internet, and besides guerilla warfare is not expensive. The local community is loyal because it is cultivated. Both Hamas and Hezbollah see themselves as social benefactors for their communities, but there are punishment beatings for those who step out of line. Indoctrination is a usual device. Whether it is readings from Marx or the Koran, it is necessary to commit your own side to one world view.
The media are the most important arm of the terrorist. I don't think that Western governments have caught on to this yet. We proudly display our independent, uncensored media, but the enemy has no such compunctions. They say, "Telling a lie is not a sin if it helps our side this war to win." The enemy has infiltrated our mainstream media. Try to discover how many at the BBC are Muslim converts. The American media lost America the Viet Nam war. The Somalia debacle and the Beirut bomb were designed to play on American television. In Iraq and Afghanistan the media are playing the same "troops out" card. Governments must be much smarter at using the media.
Are we losing the war? Not yet, but we are not winning it. We need some thinkers on duty. I have been listening to a few military strategists over the last few days. I have become convinced that at last we are putting some good minds on the problem.
Monday, September 11, 2006
Tony Blair
One of Tony Blair's problems in leaving number 10 by next summer is that he has rented out his own house in London to the film director Michael Caton Jones (he directed 'Shooting Dogs', which I have already blogged about). The director isn't due to move until 2008. The Blairs will have to rent. I am amazed that nobody had done the sums before and worked out that that was when Tony was likely to quit.
New Labor has shot itself in the foot over the past week. It's astonishing to me that party activists have not recognized what has happened over the past decade. Blair has won three elections by adopting the policies of the Conservative Party. A strong pound, balanced budgets, income tax kept low, a robust foreign policy, support for America, Euroscepticism, continued privatization. In the meantime he has kept the socialists sweet by ploughing more and more money into the National Health Service and the state education system.
His natural supporters on the left have been unhappy because of surreptitious privatization of the the NHS. New building has been funded by the private sector and leased back by the NHS. This strategy has meant that the costs don't appear on the accounts as public borrowing requirements, but the cost is much greater in the long run, because goivernment can borrow much more cheaply than industry. On teh other hand the private sector won't stand for the petty obstructionism of the Unions. Recently a contract was awarded to DHL for the purchasing of all supplies in the health service, replacing the in-house service.
Similarly in education the private sector has been invited in, in a way that displeases the Unions. The constant drive towards privatization was one of Margaret Thatcher's big ideas and Blair has stepped into her mantle. She saw him as her true succesor.
What has really done for Blair has been Iraq. The impression is that the invasion of Iraq has been a failure. Had it been a success, the argument over whether it was legal would have dissipated. Just as in a football match people are only interested in the result, so in Iraq the result is the only thing that matters, not how we played or why we went there.
There is a substantial Muslim minority, in London especially, that is solidly against Tony Blair. They form a formidable rent-a-crowd to demonstrate in London against the government. Look carefully at that crowd and you will see that apart from Muslims it comprises the Socialist Workers party, communists, Trotskyites, the Public Sector Unions, sacked ministers, members of the LSD party (Liberal-Social Democrats) and animal libbers. An alliance of all the enemies that Blair has made with all his different policies.
In fact, Blair has a very good record at settling International disputes. In Northern Ireland his performance together with Bill Clinton (and not to forget John Major) has brought peace after 700 years of fighting. In the former Yugoslavia, he has ended the persecution of Muslims. In Sierra Leone a peace has broken out after a nasty civil war. The charge in Iraq is that lies were told about weapons of mass destruction to engineer an opportunity to finish the job begun in 1990. In fact, everybody in the world (and perhaps even Saddam himself) believed there wee weapons of mass destruction in Iraq. In my view the removal of Saddam from power was entirely justifiable. Genocide is (or should be) a concern for the United Nations and defiance after many years of sanctions is itself justification for war. Had not members of the Security Council had reasons of their own for supporting the continuation of Saddam's tyranny, a coalition similar to that assembled by Bush senior would have invaded Iraq.
Look to who armed Saddam for the true culprits. No it wasn't the UK and the USA - it was Russia, France and China. If you remember there was a scandal over Reagan arming Iran.
Whatever, the rights and wrongs of the Iraq invasion, the forces are there now with a UN warrant. The current Iraq war is largely a civil war between Sunnis and Shiites. It is certainly arguable that the US post-war strategy has been remiss, but who would put their hand up and say that they would like Saddam back?
There is also criticism of Blair over Afgfhanistan. 35 British troops have been killed there. The Nato force there is 10% below strength, largely because other European powers have not fulfilled their committment. Most of the deaths can be put down to equipment failure. The Ministry of Defence has a long record of buying the wron equipment, and seems to have erred again in the use of snatch Land Rovers, developed in Belfast, where they need a vehicle with more protection against RPGs and land mines. But for those who want the troops out, think on this: they are fighting against the Taliban, the very people who harbored Usama Bin Laden, the mastermine behind 9/11. Today is the 5th anniversary of that fateful day.
When Blair goes who will we get. Most likely, at least for a couple of years, Gordon Brown. That will not please the Socialist Workers party. Brown is the architect of New Labor's privatization policies. On Iraq and Afghanistan there is not a cigarette paper between him and Blair. He is more of a Eurosceptic than Blair; it was his prevarication that saved us from the Euro. He is a confirmed Atlanticist. Compared to Blair he is fatter and not so pretty. His smile seems more forced and he is Scottish. This may be important. Since Scottish devolution, the Scottish parliament has control over most Scottish domestic policy. English domestic policy - over health, education, prisons, the law, transport, housing etc is controlled by the British parliament, a body which includes Scottish MPs. The Scottish MPs can vote in favor of things that do not concern their own electors. English electors have no remedy. They cannot vote out of power people who control their destiny. It is barely tolerable to have MPs who do this - it was the fact that there are no conservatives
in Scotland that led to the demand for a Scottish Parliament - but to have a Prime Minister who cannot be censored by the elctorate cannot be tolerated. This is known as the West Lothian question and it has been simmering. It will start to boil over shortly.
At the next elction the Liberals will be only party opposing Iraq and Afghanistan. Their current stading in the opinion polls is 16%. The were also in the Times this morninig. It seems they want to make it compulsory for cyclists to have a bell on their bicycles.
New Labor has shot itself in the foot over the past week. It's astonishing to me that party activists have not recognized what has happened over the past decade. Blair has won three elections by adopting the policies of the Conservative Party. A strong pound, balanced budgets, income tax kept low, a robust foreign policy, support for America, Euroscepticism, continued privatization. In the meantime he has kept the socialists sweet by ploughing more and more money into the National Health Service and the state education system.
His natural supporters on the left have been unhappy because of surreptitious privatization of the the NHS. New building has been funded by the private sector and leased back by the NHS. This strategy has meant that the costs don't appear on the accounts as public borrowing requirements, but the cost is much greater in the long run, because goivernment can borrow much more cheaply than industry. On teh other hand the private sector won't stand for the petty obstructionism of the Unions. Recently a contract was awarded to DHL for the purchasing of all supplies in the health service, replacing the in-house service.
Similarly in education the private sector has been invited in, in a way that displeases the Unions. The constant drive towards privatization was one of Margaret Thatcher's big ideas and Blair has stepped into her mantle. She saw him as her true succesor.
What has really done for Blair has been Iraq. The impression is that the invasion of Iraq has been a failure. Had it been a success, the argument over whether it was legal would have dissipated. Just as in a football match people are only interested in the result, so in Iraq the result is the only thing that matters, not how we played or why we went there.
There is a substantial Muslim minority, in London especially, that is solidly against Tony Blair. They form a formidable rent-a-crowd to demonstrate in London against the government. Look carefully at that crowd and you will see that apart from Muslims it comprises the Socialist Workers party, communists, Trotskyites, the Public Sector Unions, sacked ministers, members of the LSD party (Liberal-Social Democrats) and animal libbers. An alliance of all the enemies that Blair has made with all his different policies.
In fact, Blair has a very good record at settling International disputes. In Northern Ireland his performance together with Bill Clinton (and not to forget John Major) has brought peace after 700 years of fighting. In the former Yugoslavia, he has ended the persecution of Muslims. In Sierra Leone a peace has broken out after a nasty civil war. The charge in Iraq is that lies were told about weapons of mass destruction to engineer an opportunity to finish the job begun in 1990. In fact, everybody in the world (and perhaps even Saddam himself) believed there wee weapons of mass destruction in Iraq. In my view the removal of Saddam from power was entirely justifiable. Genocide is (or should be) a concern for the United Nations and defiance after many years of sanctions is itself justification for war. Had not members of the Security Council had reasons of their own for supporting the continuation of Saddam's tyranny, a coalition similar to that assembled by Bush senior would have invaded Iraq.
Look to who armed Saddam for the true culprits. No it wasn't the UK and the USA - it was Russia, France and China. If you remember there was a scandal over Reagan arming Iran.
Whatever, the rights and wrongs of the Iraq invasion, the forces are there now with a UN warrant. The current Iraq war is largely a civil war between Sunnis and Shiites. It is certainly arguable that the US post-war strategy has been remiss, but who would put their hand up and say that they would like Saddam back?
There is also criticism of Blair over Afgfhanistan. 35 British troops have been killed there. The Nato force there is 10% below strength, largely because other European powers have not fulfilled their committment. Most of the deaths can be put down to equipment failure. The Ministry of Defence has a long record of buying the wron equipment, and seems to have erred again in the use of snatch Land Rovers, developed in Belfast, where they need a vehicle with more protection against RPGs and land mines. But for those who want the troops out, think on this: they are fighting against the Taliban, the very people who harbored Usama Bin Laden, the mastermine behind 9/11. Today is the 5th anniversary of that fateful day.
When Blair goes who will we get. Most likely, at least for a couple of years, Gordon Brown. That will not please the Socialist Workers party. Brown is the architect of New Labor's privatization policies. On Iraq and Afghanistan there is not a cigarette paper between him and Blair. He is more of a Eurosceptic than Blair; it was his prevarication that saved us from the Euro. He is a confirmed Atlanticist. Compared to Blair he is fatter and not so pretty. His smile seems more forced and he is Scottish. This may be important. Since Scottish devolution, the Scottish parliament has control over most Scottish domestic policy. English domestic policy - over health, education, prisons, the law, transport, housing etc is controlled by the British parliament, a body which includes Scottish MPs. The Scottish MPs can vote in favor of things that do not concern their own electors. English electors have no remedy. They cannot vote out of power people who control their destiny. It is barely tolerable to have MPs who do this - it was the fact that there are no conservatives
in Scotland that led to the demand for a Scottish Parliament - but to have a Prime Minister who cannot be censored by the elctorate cannot be tolerated. This is known as the West Lothian question and it has been simmering. It will start to boil over shortly.
At the next elction the Liberals will be only party opposing Iraq and Afghanistan. Their current stading in the opinion polls is 16%. The were also in the Times this morninig. It seems they want to make it compulsory for cyclists to have a bell on their bicycles.
Saturday, September 09, 2006
Chlorambucil plus rituximab
Don't read this if you are squeamish.
As readers will know I have long been an advocate of chlorambucil plus rituximab as a logical regimen to study in CLL.
Trying to cure CLL is a forlorn hope in many cases. The most successful regimens at producing molecular remissions - remissions in which the most sophisticated tests available cannot detect a single CLL cell in the body - are achieved with drugs like fludarabine and Campath which are very good at killing CLL cells, but also very good at killing T cells. What no-one has shown yet is that such intensive regimens have ever cured anyone, nor even whether the overall survival with such treatment is better than starting with chlorambucil.
It may be possible to cure people with a transplant, but this is a very high risk strategy. Most people's experience is that you kill more than you cure, and the follow up of mini-transplants, which are less toxic, is too short to know how successful they are.
CLL should not be thought of as just another cancer. As a cancer it is usually not much of a player. Very few CLL sufferers are ravaged by their tumor the way that melanoma attacks you. Melanoma is no respecter of territory it careers about the body setting up colonies wherever it lands. Great black tumors appear in the lungs, the liver, the bowel wall, the muscles, the heart, the spleen, the brain - it knows no bounds. CLL cells in most people obey the rules. They keep to the highway where lymphocytes are supposed to be. They rest in lymph nodes the liver and the spleen, causing traffic jams to be sure, but seldom spilling out into adjacent fields. This is why some doctors talk about a 'good cancer'. But CLL is more than just another cancer.
CLL is the tumor that causes the greatest disruption of the immune system. Until AIDS came along it was the only disease in adults that affected the immune system in a major way. The earliest work that I did on CLL showed that even the mildest cases, stage 0 with a lymphocyte count of less than 10, had impaired immunity. They were not able to respond to a new vaccine that they had not met previously. Everybody thinks that this is an antibody problem; after all, hypogammaglobulinemia - low levels of immunoglobulin in the blood - is a characteristic finding in CLL which is a B cell disease, and the B cells are responsible for making the immunoglobulin. But it is the T cells that instruct the B cells how to make the antibodies and T cells are at fault in CLL.
So to treat CLL with drugs that further damage T cells, seems to me to be risky, if not perverse. When fludarabine or Campath are used, it is necessary to protect against the kinds of germs that T cells are there to protect you from. Pneumocystis carinii and Herpes zoster require prophylaxis with Bactrim and val- or fam- cyclovir respectively. But the story doesn't end there. After fludarabine it is extremely difficult to get a stem cell harvest for an autograft. After fludarabine autoimmune hemolytic anemia may be triggered and sometimes this is so severe as to be untreatable. After fludarabine Richter's syndrome is more likely, probably because of reactivation of EB virus. After Campath, and sometimes after fludarabine in combination reactivation of CMV occurs. After fludarabine the risk of second cancers, especially skin cancers, is increased. After fludarabine secondary myelodysplasia seems to be commoner. I strongly suspect that this is because of its effect on T cells.
The first time I lectured about fludarabine I rejoiced that here was a drug with a major effect on lymphoma that was only minimally marrow toxic. I was reminded at the time by Professor Grant Prentice that its effect on T cells might be more significant. He was right. Fludarabine, like marriage 'is not by any to be enterprised, nor taken in hand, unadvisedly, lightly, or wantonly'. No doubt there are some for whom it is the right thing, but for many we must, like the dentist in 'Marathon Man', ask the question, "Is it safe?"
Don't you find it surprising that despite producing more and better responses and longer remissions than chlorambucil, it does not lead to a longer overall survival? Fludarabine's supporters put it down to crossover, the fact that once they fail chlorambucil, patients can try fludarabine later. But if that were the cause you would expect some to fall by the wayside in the changeover, and although it might not be significant, I would expect a small gap to be opening up at 5 years showing a small benefit for fludarabine. In fact, the small, but still statistically insignificant gap seems to be opening up in favor of chlorambucil. One possible reason for the failure of fludarabine based regimens to show superiority is the occurrence of late complications.
Rituximab is a different matter. Although as a single agent it does not seem to be all that good in CLL, in combination with virtually any chemotherapy, it adds value. It is so non-toxic. Sure it gets rid of the B cells, but not for ever as they are rapidly replenished from a CD20 negative source. Sure it causes infusion reactions, but these can be abolished by giving it more slowly. So adding it to chemotherapy improves the response and the overall survival. CHOP-R is better than CHOP; CVP-R is better than CVP; FCR is better than FC.
I have noticed that physicians have started using CVP-R for CLL. The logic behind this is that in follicular lymphoma CVP-R is better than CVP in the Robert Marcus trial. To many oncologists one low grade lymphoma is very like another and CLL is regarded as just another low grade lymphoma. I have no doubt that CVP-R will work in CLL, but CVP has been trialed in CLL and been shown to be no better than chlorambucil in terms of responses and survival, but worse in two respects: cyclophosphamide is more likely to cause you to lose your hair, and vincristine causes peripheral neuropathy. Everybody on vincristine loses their ankle reflexes, and some, especially older patients, never walk again.
Chlorambucil has been around since 1951. There is no money in it for the pharmaceutical companies. It is one sixteenth the price of fludarabine. Before fludarabine came along it had beaten off CVP, CHOP and CEP. The trials that showed it to be worse in some respects than fludarabine used a sub-optimal dose of chlorambucil. The latest CLL4 trial in Britain actually shows no difference between chlorambucil and fludarabine, though FC is better in every respect, except in overall survival.
Chlorambucil is not the perfect drug. It is marrow toxic, especially in higher doses. CLL does become resistant to it in a proportion of cases. It causes a rash in about 2% of cases. It does suppress T cells to a degree, though nothing like as much as fludarabine or Campath.
So why has nobody tried chlorambucil plus rituximab? There has been a small phase II trial in low grade lymphoma (unlike the Robert Marcus trial, this did include some patients with CLL). This trial was encouraging.
FCR has captured so much of the market and is so impressive up front that we have not been paying enough intention to late complications. Furthermore, the way it has developed, with initial courses given in Houston and subsequent courses and follow up taking place elsewhere in the US (indeed elsewhere the world) militates against the detection of late complications. Why was it that Houston, the greatest user of fludarabine, did not pick up the complication of triggering autoimmune complications as early as others? Because the follow-up was scattered to the winds.
The slow movement towards trying chlorambucil plus rituximab has come from patients, especially those who pay attention to the internet.
Here is a prediction. Changes in Big Pharma will bring about chlorambucil plus rituximab trials. Schering AG, a relatively small German company which markets both fludarabine and Campath, has been taken over by Bayer, one of the giants of the industry. This makes it much more unlikely that there will be joint trials between the Rituximab manufacturers and the fludarabine manufacturers in the future. There was always the possibility that Roche would take over Schering, but Bayer is too big a mouthful. So Roche, which handles rituximab outside the US, will be looking for another drug to use with rituximab. I predict they will hit on chlorambucil.
About 40% of patients with mutated IgVH genes will require some sort of therapy. Many of them will be elderly. The last thing they want is their immune systems completely scuppered. I predict that it will be in this group that we see the first trials.
As readers will know I have long been an advocate of chlorambucil plus rituximab as a logical regimen to study in CLL.
Trying to cure CLL is a forlorn hope in many cases. The most successful regimens at producing molecular remissions - remissions in which the most sophisticated tests available cannot detect a single CLL cell in the body - are achieved with drugs like fludarabine and Campath which are very good at killing CLL cells, but also very good at killing T cells. What no-one has shown yet is that such intensive regimens have ever cured anyone, nor even whether the overall survival with such treatment is better than starting with chlorambucil.
It may be possible to cure people with a transplant, but this is a very high risk strategy. Most people's experience is that you kill more than you cure, and the follow up of mini-transplants, which are less toxic, is too short to know how successful they are.
CLL should not be thought of as just another cancer. As a cancer it is usually not much of a player. Very few CLL sufferers are ravaged by their tumor the way that melanoma attacks you. Melanoma is no respecter of territory it careers about the body setting up colonies wherever it lands. Great black tumors appear in the lungs, the liver, the bowel wall, the muscles, the heart, the spleen, the brain - it knows no bounds. CLL cells in most people obey the rules. They keep to the highway where lymphocytes are supposed to be. They rest in lymph nodes the liver and the spleen, causing traffic jams to be sure, but seldom spilling out into adjacent fields. This is why some doctors talk about a 'good cancer'. But CLL is more than just another cancer.
CLL is the tumor that causes the greatest disruption of the immune system. Until AIDS came along it was the only disease in adults that affected the immune system in a major way. The earliest work that I did on CLL showed that even the mildest cases, stage 0 with a lymphocyte count of less than 10, had impaired immunity. They were not able to respond to a new vaccine that they had not met previously. Everybody thinks that this is an antibody problem; after all, hypogammaglobulinemia - low levels of immunoglobulin in the blood - is a characteristic finding in CLL which is a B cell disease, and the B cells are responsible for making the immunoglobulin. But it is the T cells that instruct the B cells how to make the antibodies and T cells are at fault in CLL.
So to treat CLL with drugs that further damage T cells, seems to me to be risky, if not perverse. When fludarabine or Campath are used, it is necessary to protect against the kinds of germs that T cells are there to protect you from. Pneumocystis carinii and Herpes zoster require prophylaxis with Bactrim and val- or fam- cyclovir respectively. But the story doesn't end there. After fludarabine it is extremely difficult to get a stem cell harvest for an autograft. After fludarabine autoimmune hemolytic anemia may be triggered and sometimes this is so severe as to be untreatable. After fludarabine Richter's syndrome is more likely, probably because of reactivation of EB virus. After Campath, and sometimes after fludarabine in combination reactivation of CMV occurs. After fludarabine the risk of second cancers, especially skin cancers, is increased. After fludarabine secondary myelodysplasia seems to be commoner. I strongly suspect that this is because of its effect on T cells.
The first time I lectured about fludarabine I rejoiced that here was a drug with a major effect on lymphoma that was only minimally marrow toxic. I was reminded at the time by Professor Grant Prentice that its effect on T cells might be more significant. He was right. Fludarabine, like marriage 'is not by any to be enterprised, nor taken in hand, unadvisedly, lightly, or wantonly'. No doubt there are some for whom it is the right thing, but for many we must, like the dentist in 'Marathon Man', ask the question, "Is it safe?"
Don't you find it surprising that despite producing more and better responses and longer remissions than chlorambucil, it does not lead to a longer overall survival? Fludarabine's supporters put it down to crossover, the fact that once they fail chlorambucil, patients can try fludarabine later. But if that were the cause you would expect some to fall by the wayside in the changeover, and although it might not be significant, I would expect a small gap to be opening up at 5 years showing a small benefit for fludarabine. In fact, the small, but still statistically insignificant gap seems to be opening up in favor of chlorambucil. One possible reason for the failure of fludarabine based regimens to show superiority is the occurrence of late complications.
Rituximab is a different matter. Although as a single agent it does not seem to be all that good in CLL, in combination with virtually any chemotherapy, it adds value. It is so non-toxic. Sure it gets rid of the B cells, but not for ever as they are rapidly replenished from a CD20 negative source. Sure it causes infusion reactions, but these can be abolished by giving it more slowly. So adding it to chemotherapy improves the response and the overall survival. CHOP-R is better than CHOP; CVP-R is better than CVP; FCR is better than FC.
I have noticed that physicians have started using CVP-R for CLL. The logic behind this is that in follicular lymphoma CVP-R is better than CVP in the Robert Marcus trial. To many oncologists one low grade lymphoma is very like another and CLL is regarded as just another low grade lymphoma. I have no doubt that CVP-R will work in CLL, but CVP has been trialed in CLL and been shown to be no better than chlorambucil in terms of responses and survival, but worse in two respects: cyclophosphamide is more likely to cause you to lose your hair, and vincristine causes peripheral neuropathy. Everybody on vincristine loses their ankle reflexes, and some, especially older patients, never walk again.
Chlorambucil has been around since 1951. There is no money in it for the pharmaceutical companies. It is one sixteenth the price of fludarabine. Before fludarabine came along it had beaten off CVP, CHOP and CEP. The trials that showed it to be worse in some respects than fludarabine used a sub-optimal dose of chlorambucil. The latest CLL4 trial in Britain actually shows no difference between chlorambucil and fludarabine, though FC is better in every respect, except in overall survival.
Chlorambucil is not the perfect drug. It is marrow toxic, especially in higher doses. CLL does become resistant to it in a proportion of cases. It causes a rash in about 2% of cases. It does suppress T cells to a degree, though nothing like as much as fludarabine or Campath.
So why has nobody tried chlorambucil plus rituximab? There has been a small phase II trial in low grade lymphoma (unlike the Robert Marcus trial, this did include some patients with CLL). This trial was encouraging.
FCR has captured so much of the market and is so impressive up front that we have not been paying enough intention to late complications. Furthermore, the way it has developed, with initial courses given in Houston and subsequent courses and follow up taking place elsewhere in the US (indeed elsewhere the world) militates against the detection of late complications. Why was it that Houston, the greatest user of fludarabine, did not pick up the complication of triggering autoimmune complications as early as others? Because the follow-up was scattered to the winds.
The slow movement towards trying chlorambucil plus rituximab has come from patients, especially those who pay attention to the internet.
Here is a prediction. Changes in Big Pharma will bring about chlorambucil plus rituximab trials. Schering AG, a relatively small German company which markets both fludarabine and Campath, has been taken over by Bayer, one of the giants of the industry. This makes it much more unlikely that there will be joint trials between the Rituximab manufacturers and the fludarabine manufacturers in the future. There was always the possibility that Roche would take over Schering, but Bayer is too big a mouthful. So Roche, which handles rituximab outside the US, will be looking for another drug to use with rituximab. I predict they will hit on chlorambucil.
About 40% of patients with mutated IgVH genes will require some sort of therapy. Many of them will be elderly. The last thing they want is their immune systems completely scuppered. I predict that it will be in this group that we see the first trials.
Friday, September 08, 2006
Hiatus
My father-in-law is 93. Earler this week he was taken into hospital gravely ill. The hospital is 80 miles away and we have been traveling back and forth, often more than once a day. So, no blogging for the moment.
Subscribe to:
Posts (Atom)